Retinal Detachment — Emergency Surgery in London
A new shadow, curtain, flashes or a sudden increase in floaters needs urgent eye assessment. If you have been diagnosed with a retinal detachment, Mr Henderson can explain the treatment options and discuss the expected recovery for your eye. Do not wait for a reply to an online enquiry if symptoms are sudden.
Understanding Retinal Detachment
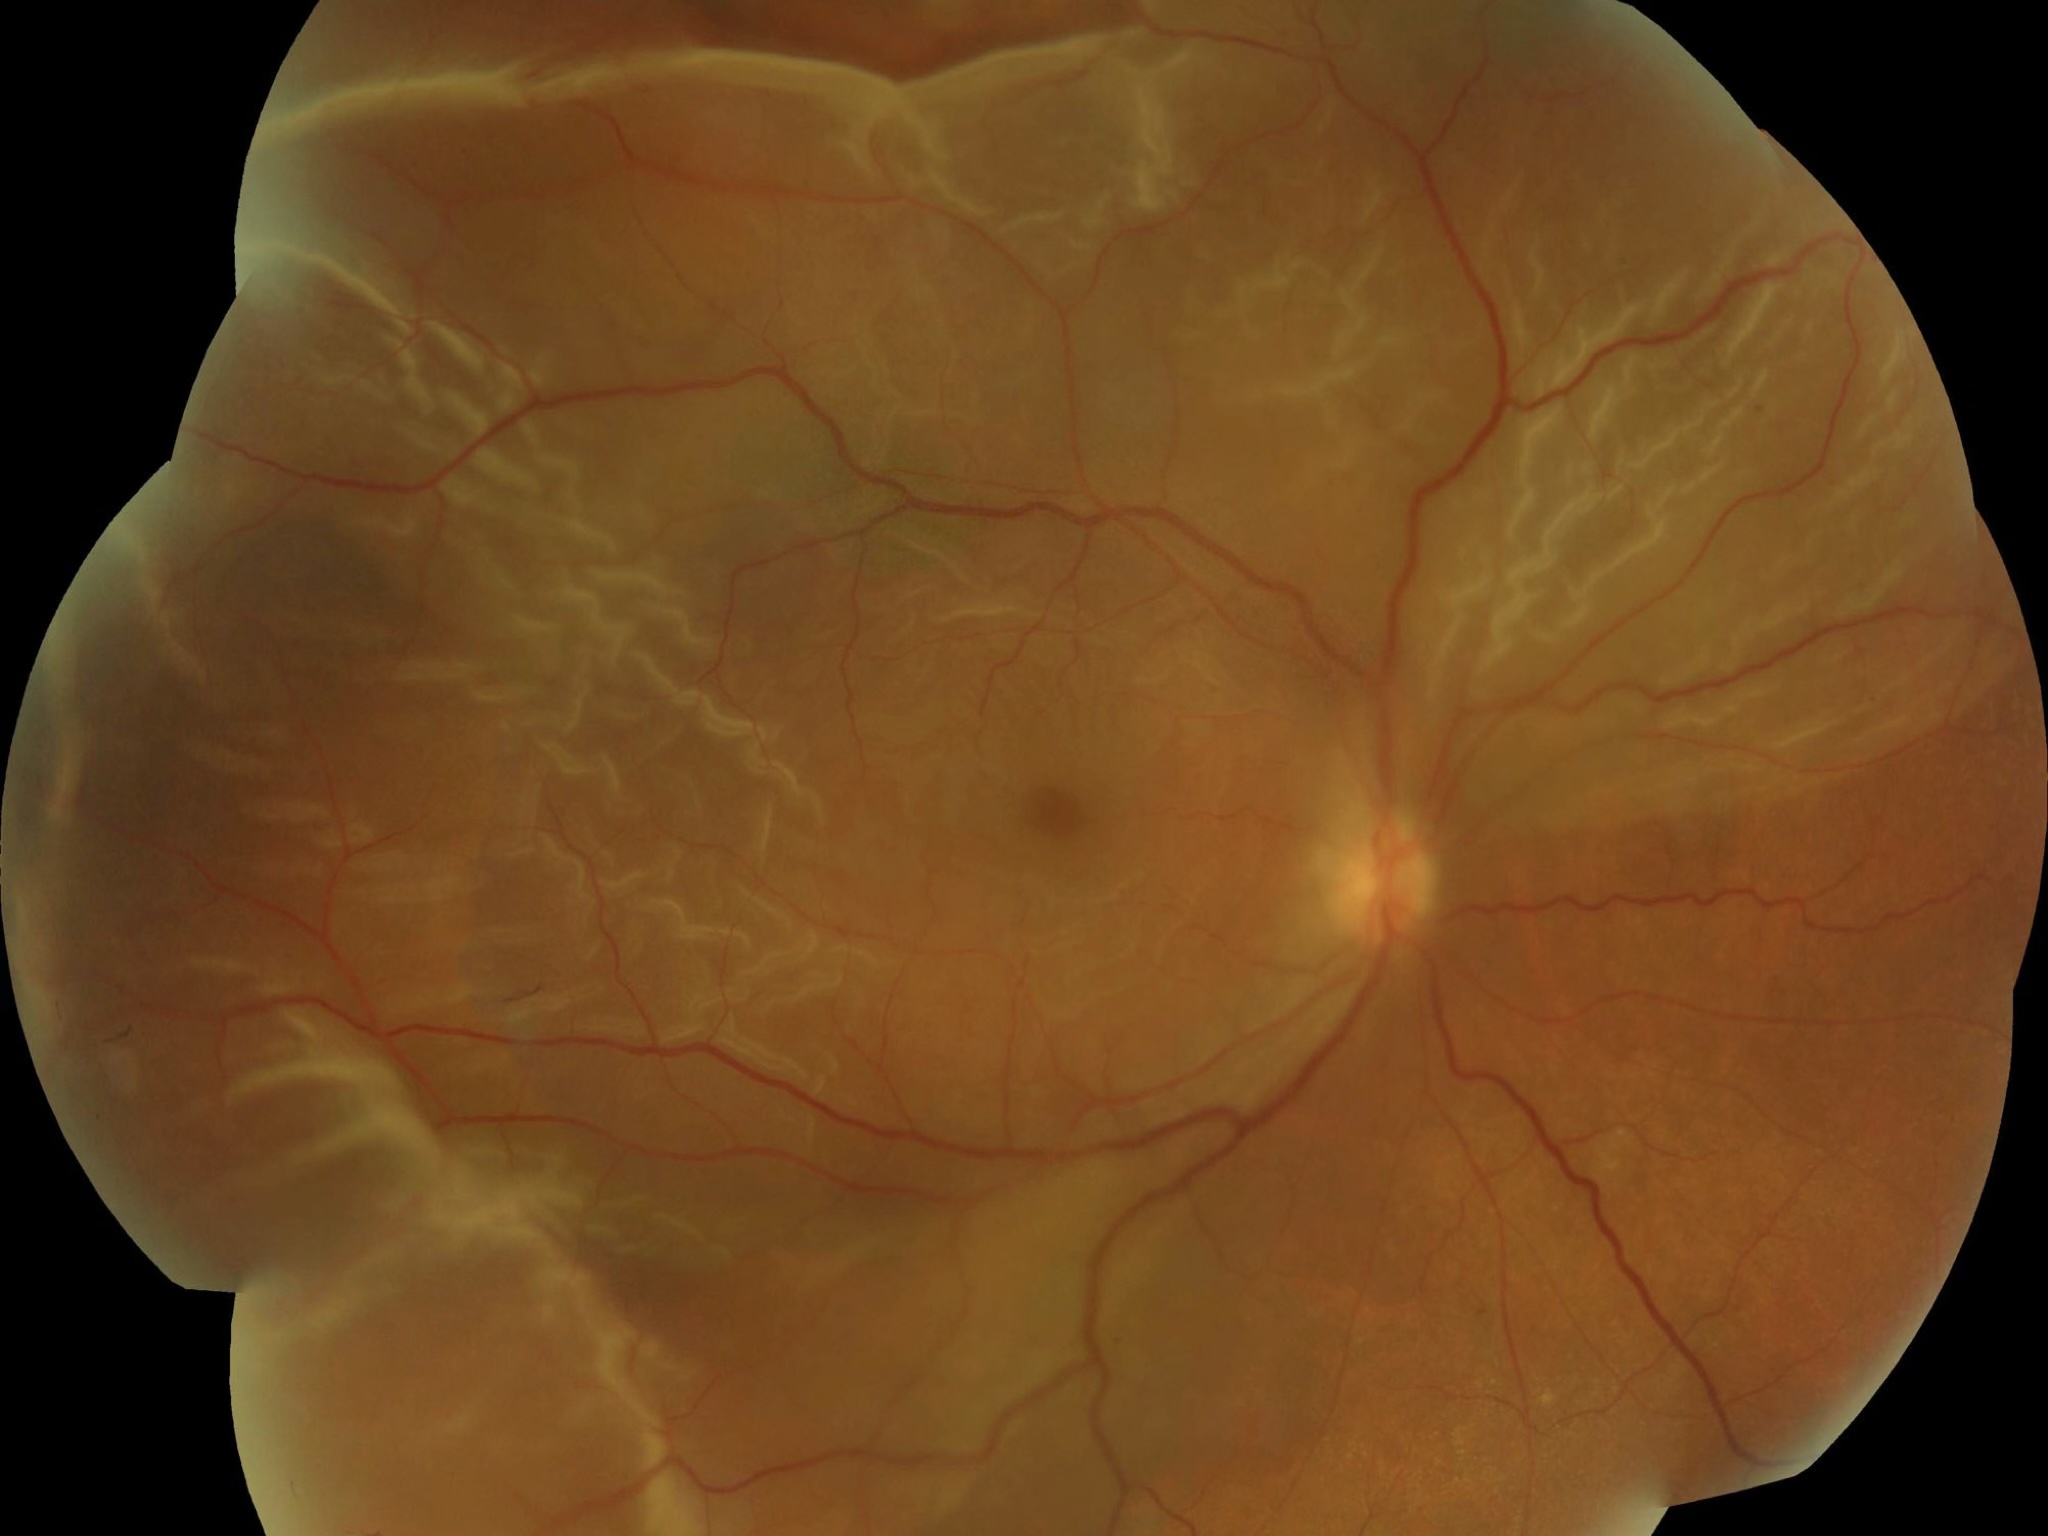
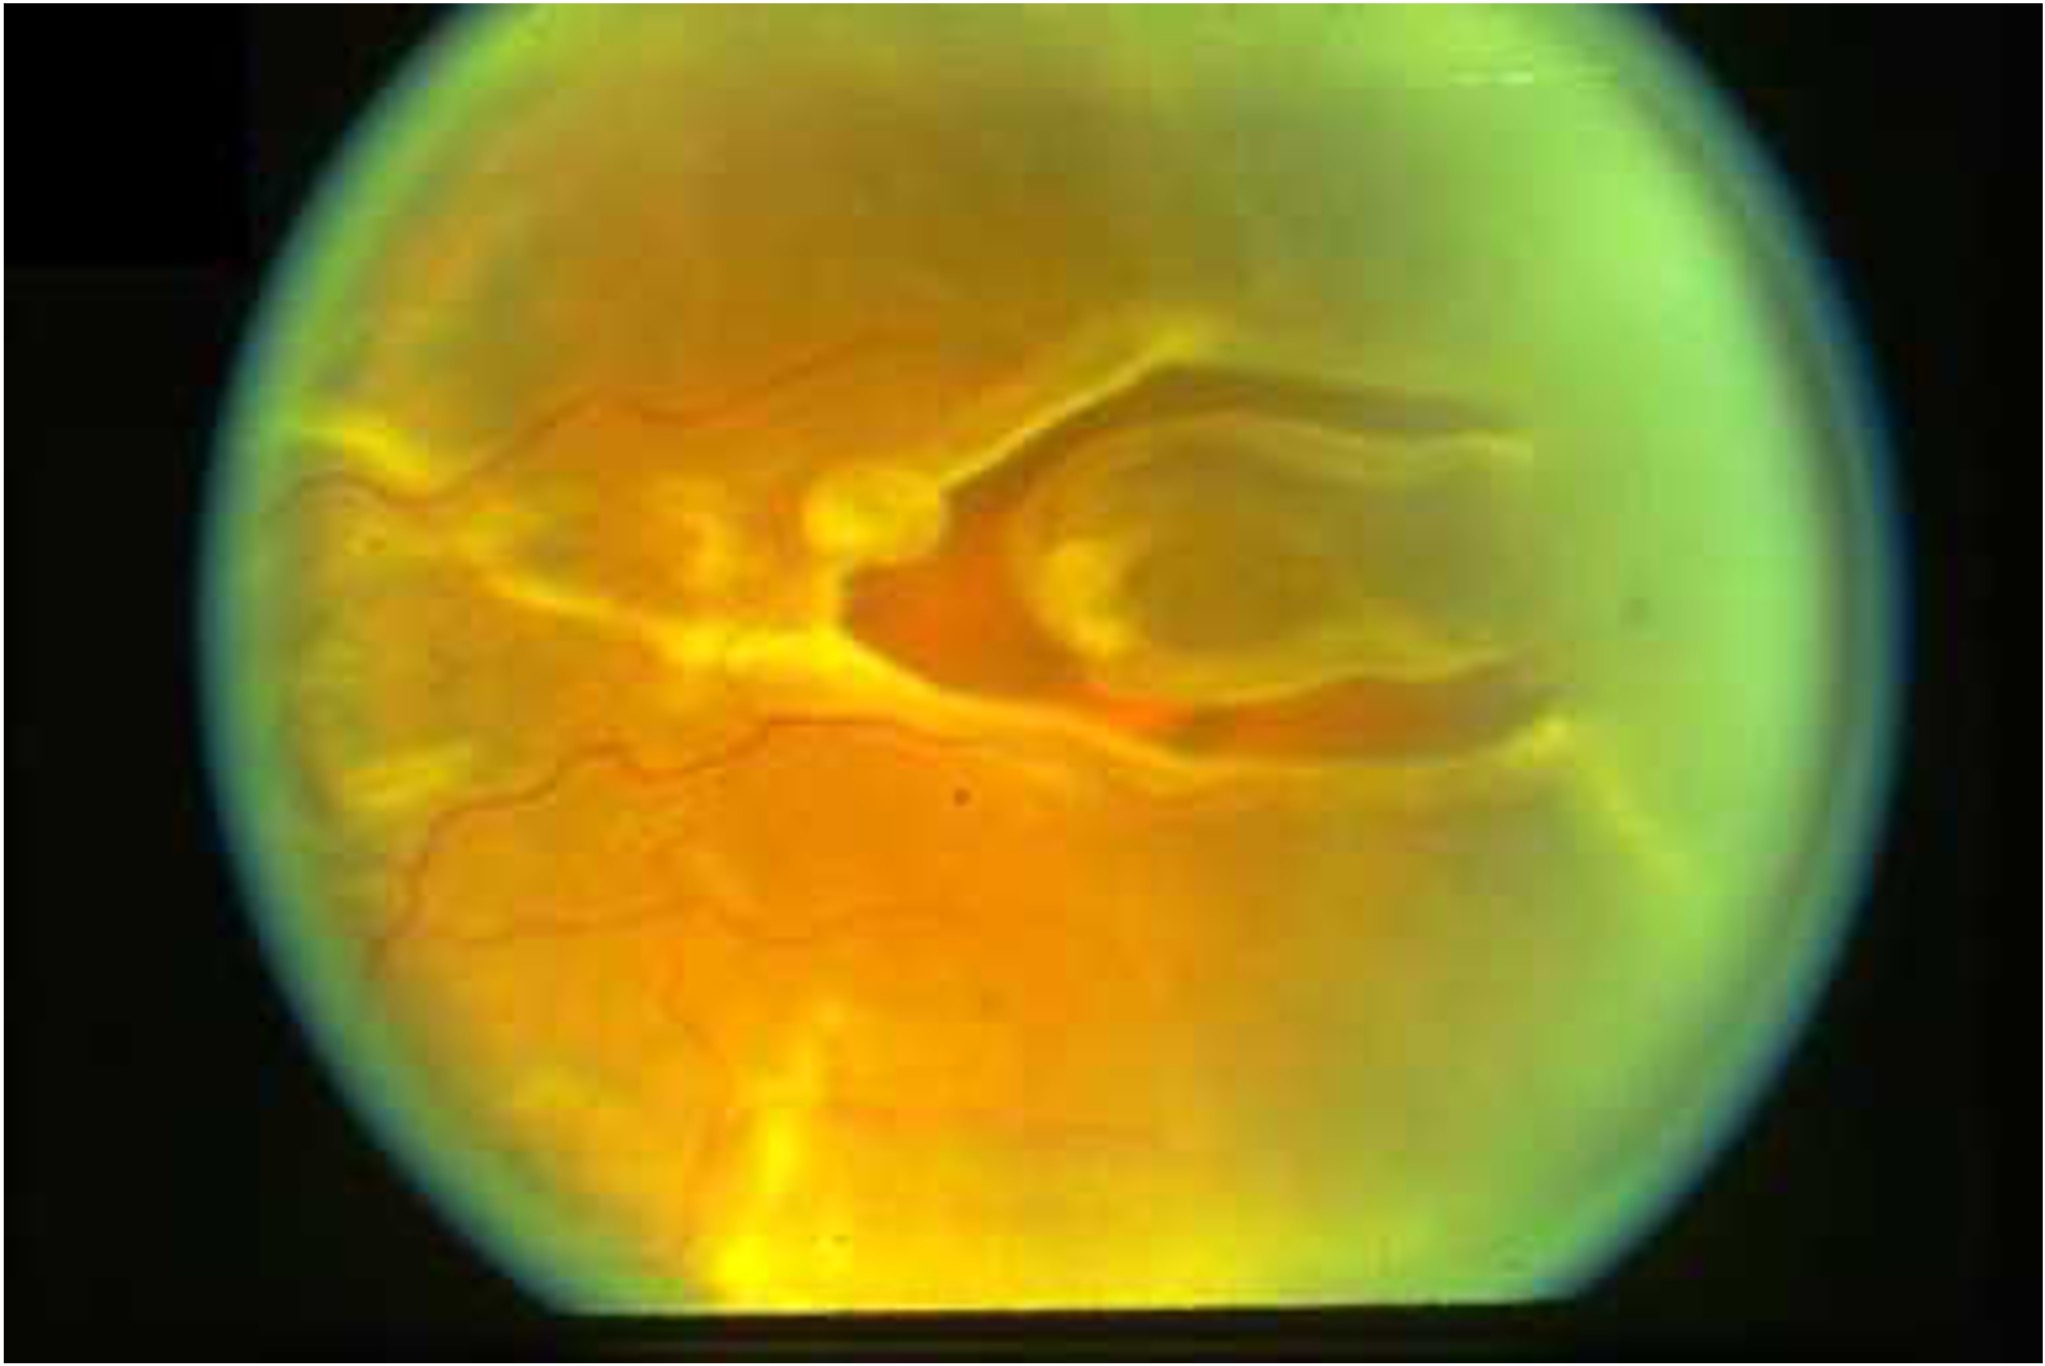
The retina is a thin layer of light-sensitive tissue lining the inside of the eye. Like wallpaper peeling from a wall, a detached retina separates from its underlying support layer — the retinal pigment epithelium — cutting off its blood supply and causing rapid, irreversible cell death.
The most common type is a rhegmatogenous retinal detachment, caused by a tear or hole in the retina that allows fluid from the vitreous cavity to seep underneath and lift the retina away. Risk factors include short-sightedness (myopia), previous eye surgery, eye trauma, and a family history of retinal detachment.
Symptoms to Watch For
Symptoms can develop suddenly and progress rapidly. Knowing the warning signs can be sight-saving.
Surgical Repair
All retinal detachments require surgery. The goal is to close the tear or tears responsible for the detachment, drain the fluid underneath, and reattach the retina to the back of the eye. Mr Henderson selects the most appropriate technique based on the pattern of detachment, the location of the tear, and the individual patient.
“The most important factor in achieving a good visual outcome is speed — the sooner a detachment is repaired before the macula detaches, the better the prognosis for central vision.”
Where the macula has already detached, surgery is still worthwhile and frequently results in meaningful visual recovery, though the final outcome takes longer to determine.
Surgical Techniques
Your Journey from Diagnosis to Recovery
Urgent eye assessment, examination and imaging as appropriate. Do not wait for a response to this website if you have sudden symptoms.
Mr Henderson personally reviews your case and selects the technique best suited to your detachment — vitrectomy, scleral buckle, or pneumatic retinopexy.
All surgery is performed personally by Mr Henderson in the specialist theatres at Moorfields Eye Hospital — the world’s foremost eye hospital.
Most patients go home the same day. Mr Henderson follows your recovery personally, with structured appointments to monitor healing and vision.
Vitrectomy
The most versatile approach. The vitreous gel is removed, the retina reattached, and a gas or silicone oil tamponade used to hold it in place while it heals. Suitable for the majority of detachments.
Scleral Buckle
A silicone band is sutured around the outside of the eye to indent the wall, closing the tear from the outside. Particularly effective for younger patients and specific tear patterns.
Pneumatic Retinopexy
A gas bubble is injected into the eye and the patient positions to push the bubble against the tear. Suitable for selected cases with a single superior tear and minimal fluid.
Frequently Asked Questions